John Brewer discovered his dangerous heart rhythm on an operating table, mid-procedure. A new analysis of retinal scans from more than 90,000 people says the warning had been printed on the back of his eyeball for years — and that a routine trip to the optician might one day catch it before the stroke does.
LONDON
John Brewer went into Moorfields Eye Hospital this year for a cataract operation. Routine. Sedation, twenty minutes, home for tea.
Partway through, the surgical team stopped. Something was wrong with his heart. The rhythm had gone erratic on the monitors. The procedure was paused mid-operation while staff hooked him up to an electrocardiogram, which confirmed what they suspected: John was in atrial fibrillation — the most common heart rhythm disorder in the world, and one of the most dangerous. Medication was given so the operation could be finished safely. He was referred straight to a cardiologist, who has since confirmed the diagnosis.
"It would have been so much easier if my atrial fibrillation had been detected earlier through a routine retinal scan at one of my regular appointments," John says, "rather than on the operating table, which was a very distressing experience for my wife and I."
Here is the thing that turns John Brewer's bad afternoon into a story with national implications. According to research led by University College London and Moorfields Eye Hospital, the evidence of his heart condition may well have been sitting in the back of his eye — visible on a scan he had already had — for as long as four years before anybody noticed.
NINETY THOUSAND EYES
The study, published in PLOS Digital Health, is the largest of its kind ever attempted. The team, led by Dr Josef Huemer with Dr Siegfried Wagner as senior author, both of the UCL Institute of Ophthalmology and Moorfields Eye Hospital NHS Foundation Trust, pulled retinal imaging data on more than 90,000 people from two entirely separate datasets.
The first was AlzEye, a retrospective Moorfields cohort of 50,651 patients aged 40 and over, imaged between 2008 and 2018. Of those, 5,375 — about 11 per cent — already had atrial fibrillation.
The second was UK Biobank, a prospective study of around 39,000 participants aged 40 to 69, recruited between 2006 and 2010.
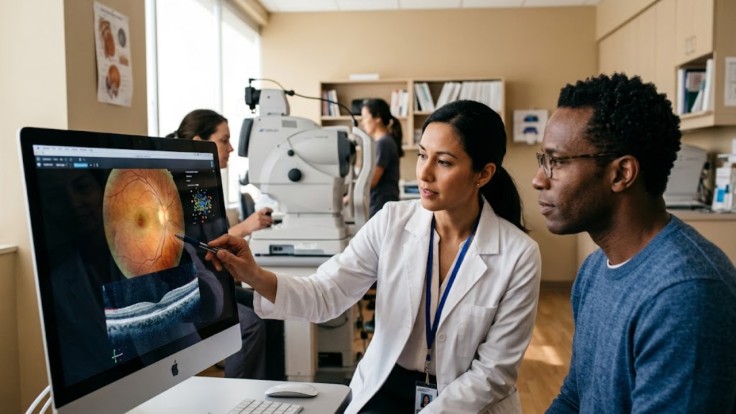
From each person the researchers extracted two kinds of picture: optical coherence tomography scans, which slice through the retina and measure the thickness of its individual layers to the micrometre, and colour retinal photographs, from which they measured the calibre and branching complexity of the tiny blood vessels.
Then they asked a simple question. Do the eyes of people with atrial fibrillation look different?
WHAT THEY FOUND
They do. Consistently, and across both datasets.
In the AlzEye cohort, people with atrial fibrillation had a significantly thinner macular ganglion cell-inner plexiform layer — the mGCIPL, a band of nerve cells at the back of the eye that connect the retina to the brain. The difference was 1.96 micrometres thinner, with a 95 per cent confidence interval of 1.58 to 2.34.
That sounds like nothing. It is roughly one fiftieth the width of a human hair. But it was replicated independently in UK Biobank, where the same layer was 1.19 micrometres thinner in people with atrial fibrillation, confidence interval 0.65 to 1.73.
Other layers were affected too. The macular retinal nerve fibre layer was 0.69 micrometres thinner. The inner nuclear layer was down 0.57 micrometres, the photoreceptor layer down 0.93. The retinal venules were narrower, and their branching pattern — measured as fractal dimension — was less complex, while the arteriolar branching was in fact more complex.
Then came the part that made headlines. Among the 39,013 UK Biobank participants who had no atrial fibrillation at all when their eyes were photographed, 838 went on to develop it over an average of four years. And their retinas had already been thinner at baseline.
After adjusting for age, sex, ethnicity, hypertension, diabetes, alcohol consumption and smoking status, every standard-deviation decrease in mGCIPL thickness was associated with a 27 per cent increased hazard of developing atrial fibrillation. The 95 per cent confidence interval ran from 5 per cent to 54 per cent.
In other words: the eye knew first.
WHY WOULD AN EYE KNOW ABOUT A HEART?
The retina is not really part of the eye in the way most people assume. Embryologically it is brain tissue — an outpost of the central nervous system pushed forward to the front of the skull, complete with its own dedicated microvasculature. It is the only place in the entire human body where a doctor can look directly at living blood vessels and living nerve cells without cutting anything open.
That is the whole premise of the field these researchers work in, which has been given the name oculomics: the eye as a window onto systemic disease.
As for the mechanism, the authors have a specific and rather chilling hypothesis. Atrial fibrillation causes blood to pool in the upper chambers of the heart, where it can clot. Small clots travel. Most of the time nobody notices — they produce silent micro-strokes that leave no obvious symptom but do quietly kill off small patches of brain tissue.
The team propose that the retinal thinning they measured is the visible shadow of exactly those events: reduced blood flow to the retinal nerve cells, causing them to atrophy, as a downstream consequence of an arrhythmia nobody has yet diagnosed.
If they are right, then a thinning retinal layer is not merely a marker of risk. It is evidence that damage has already begun.
THE CONDITION THAT HIDES
Atrial fibrillation affects more than 1.5 million people in the United Kingdom alone. It substantially raises the risk of stroke, heart failure and death.
The reason it matters so much that John Brewer's was caught by accident is that accidental discovery is depressingly normal. Atrial fibrillation is often paroxysmal — it comes and goes. A standard electrocardiogram captures perhaps thirty seconds of heart rhythm. If the heart happens to be behaving during those thirty seconds, the test comes back clean.
The result is a large reservoir of people walking around with an undiagnosed, treatable condition that is steadily loading the gun. US modelling has estimated that around 11 to 13 per cent of all atrial fibrillation cases are undiagnosed, and that more than half of that undiagnosed group were at moderate to high risk of stroke — 77 per cent had a CHADS2 score of 1 or more, and 56 per cent scored 2 or higher.
Meanwhile, almost a third of all ischaemic strokes are classified as cryptogenic — meaning nobody can identify the cause. Silent atrial fibrillation is believed to be a major contributor.
This is the gap the Moorfields team is aiming at. Not replacing the ECG. Filling in the enormous space around it.
THE MACHINE IS ALREADY IN THE HIGH STREET
The most commercially interesting feature of this research is that it requires no new equipment whatsoever.
Optical coherence tomography scanners are already installed in high-street opticians across Britain and in eye clinics worldwide. Millions of people already sit in front of one every year, usually to check for glaucoma or macular degeneration, often as a paid add-on to a routine sight test. The scan takes seconds, involves no needles, no radiation and no dye, and the patient simply looks at a light.
"This large-scale analysis shows that retinal imaging can pick up on structural changes within the eye that are clearly linked to atrial fibrillation," says Dr Siegfried Wagner. "For patients, the value of this kind of eye imaging is that it is easy to access, quick and doesn't involve any invasive procedures. Although not intended to replace ECG-based diagnosis, retinal imaging could act as a complementary tool, catching those most at risk of atrial fibrillation before it causes real harm."
Lead author Dr Josef Huemer is careful about the conditional. "If confirmed in further research, our findings raise the possibility that routine eye examinations could, in future, help identify people who would benefit from closer cardiac assessment, potentially enabling earlier treatment with therapies known to reduce the risk of stroke."
That last clause is the prize. Atrial fibrillation-related strokes are largely preventable with anticoagulation. A person identified early and started on a blood thinner is a person who does not lose the use of their left side at 68.
WHAT THIS STUDY DOES NOT SHOW
Before anybody books an emergency eye test, the limitations deserve the same billing as the findings.
This is an observational association study, not a screening trial. Nobody was randomly assigned to have their retina scanned. Nobody's outcomes were changed. The researchers looked backwards and sideways through existing data.
The effect sizes are small in absolute terms — one to two micrometres — and there is substantial overlap between the groups. Plenty of people with thin retinal layers will never develop atrial fibrillation, and plenty with thick ones will. The hazard ratio's confidence interval, running from 5 per cent to 54 per cent, is wide enough to be consistent with a fairly modest effect.
Retinal thinning is also not specific. The same layer thins in glaucoma, in diabetes, in Alzheimer's disease, in Parkinson's, and simply with age. Any real-world screening tool would have to separate a cardiac signal from all of that noise — and this paper does not deliver such a tool. It delivers the evidence that one might be buildable.
Atrial fibrillation status in both cohorts was ascertained from self-report and hospital admission records, which will inevitably have missed some cases — a limitation that, if anything, argues the true signal could be stronger than measured.
And a note on interests, as any reader is entitled to: several authors declare extensive industry relationships. Professor Pearse Keane, the AlzEye chief investigator, is a co-founder of Cascader Ltd and an equity owner in Big Picture Medical, and has consulted for Roche, Topcon, Boehringer Ingelheim and others. Professor Dipak Kotecha, a co-author and a leading atrial fibrillation trialist, reports grants from the NIHR, the British Heart Foundation and multiple EU consortia involving pharmaceutical partners. The study itself was funded by the National Institute for Health and Care Research and Moorfields Eye Charity, and the funders had no role in its design or publication.
It went through peer review over five months — received 8 March 2026, accepted 27 July, published 10 September.
THIRTY MILLION IMAGES
None of this would be possible without an unglamorous piece of infrastructure: the INSIGHT Eye and Oculomics Health Data Research Hub, run by Moorfields Eye Hospital NHS Foundation Trust and the UCL Institute of Ophthalmology.
INSIGHT is the world's largest ophthalmic imaging bioresource — more than 30 million eye images, linked to medical records. It exists because the NHS has been photographing British retinas at scale for years and, unusually, kept the pictures in a form researchers can actually use.
The same team has already mined that resource to identify early signs and predict progression in age-related macular degeneration, glaucoma and diabetic retinopathy, and to find retinal markers for Parkinson's disease, Alzheimer's disease, schizophrenia, cardiovascular disease and stroke.
Atrial fibrillation is simply the latest entry on a list that is getting uncomfortably long — and which raises a question the health service has not yet properly answered. If your optician's scanner can see the beginnings of your dementia, your stroke risk and now your heart arrhythmia, who is supposed to tell you? And what happens to the millions of scans already sitting on hard drives, taken before anybody knew what to look for?
WHAT THIS MEANS FOR YOU
Nothing changes at your next eye test. No optician in Britain is currently scanning for atrial fibrillation, and none should be on the strength of one observational study.
What should change is your index of suspicion about your own heart rhythm. Atrial fibrillation is diagnosable at home: take your pulse at the wrist for a full minute when you are sitting quietly. A rhythm that is irregularly irregular — no pattern to the irregularity at all — is worth mentioning to a GP. Many modern smartwatches and cheap fingertip monitors will flag it too, and a single-lead ECG in a pharmacy costs very little.
Know the symptoms that people dismiss: palpitations, unexplained breathlessness, sudden drops in exercise tolerance, dizziness, or a fluttering sensation in the chest that comes and goes. And know that a substantial proportion of people have no symptoms at all.
Pay attention to the risk factors you can move. High blood pressure is the biggest modifiable driver of atrial fibrillation. Heavy alcohol use, obesity, untreated sleep apnoea and poorly controlled diabetes all raise the odds.
If you already have a diagnosis, the single most important conversation is about anticoagulation — whether you need it, and whether you are actually taking it. That is where the stroke prevention lives.
THE LAST WORD
John Brewer's story has a reasonable ending. The operation was completed. The cardiologist saw him. The diagnosis is made and can now be managed.
A great many people do not get that version. They get the one where the first symptom of a heart rhythm nobody detected is a stroke on a Tuesday morning.
What the Moorfields and UCL team have shown is that, for some of those people, the information was there. Recorded. Digitised. Sitting in a file at a high-street optician, four years early, in a layer of nerve cells one fiftieth the width of a hair.
Nobody knew to look. Now, perhaps, they will.
Published By | Features Editor